


There’s a child in a classroom right now who cannot stop fidgeting. His teacher has asked him three times to sit still. He’s trying. He physically cannot.
Across town, a woman in her forties has just left her third massage appointment this month. Her neck and shoulders are locked again. They’re always locked. No one can explain why.
A teenager sits in front of an exam paper. She’s brilliant in conversation, witty, insightful, fast. But the words won’t come through her pen. Her hand cramps. The letters reverse. She’ll get a grade that doesn’t reflect anything she actually knows.
An elderly gentleman has just finished up 12 weeks of physical therapy for knee replacement #1, and is gearing up, emotionally and physically for knee replacement #2, following an osteoarthritis diagnosis that finally explains the excruciating pain he’s endured for the better part of 3 decades.
And in a living room on a Saturday morning, a toddler screams at the sound of a blender. Not a startled cry, a full-body, inconsolable, terrified scream. Every time. Every sound.
These look like four completely unrelated problems. They’re not.
The thread connecting them is something most people have never heard of: primitive reflexes. And once you understand what they are, how they work, and what happens when they don’t “retire on schedule”, a great deal of human struggle that previously looked like “anxiety” or “sensory issues” or “aging” or “just the way I am” begins to make a different kind of sense.
What Are Primitive Reflexes?
Primitive reflexes are automatic, involuntary movement patterns that originate in the brainstem, the oldest, deepest part of the brain. They begin developing in the womb, some as early as the second month of pregnancy, and every healthy baby is born with a full set. They are, quite literally, a sign that the nervous system is working (Capute et al., 1978; Zafeiriou, 2004). I call them our very own “super powers”.
Each reflex serves a specific survival or developmental function. The rooting reflex helps a newborn find the breast. The grasping reflex secures a baby’s hold. The Moro reflex, the infant’s startle response, alerts the body to sudden change. The Tonic Labyrinthine Reflex helps establish the baby’s relationship with gravity. The Asymmetric Tonic Neck Reflex coordinates head and hand movement, laying the groundwork for eye-hand coordination. Every one of them has a job (Goddard, 2005; Blomberg, 2015).
And every one of them is meant to be temporary.
In typical development, each primitive reflex emerges, does its work, and then integrates, meaning it is absorbed into more mature, voluntary, life-long movement patterns. Integration is not disappearance. Think of it like scaffolding: essential while the building goes up, but it needs to come down for the building to function. The primitive reflex pattern doesn’t vanish; it becomes part of the foundation on which more complex, flexible, voluntary movement is built (Goddard, 2005; Zafeiriou, 2004).
When primitive reflexes integrate properly, they are replaced by postural reflexes, the mature, lifelong patterns that give us balance, coordination, stability, and the ability to move through the world without having to think about every adjustment the body makes. This transition is the hallmark of healthy neurological development in the first year of life, and it is documented across the standard pediatric literature (Capute et al., 1978; Zafeiriou, 2004; Arcilla & Vilella, 2025).
But sometimes the transition doesn’t complete.
When a primitive reflex doesn’t integrate on schedule, it stays active in the background. It doesn’t just sit there quietly, it interferes with the more mature patterns trying to develop on top of it. The body is trying to run sophisticated software on an operating system that hasn’t finished installing.
A retained primitive reflex is like a program running in the background of your nervous system: you can’t see it, but it’s using up processing power and creating glitches you can’t explain.
Why Do Reflexes Fail to Integrate?
The integration process depends on movement, specifically, the repetitive, rhythmic, whole-body movements that babies naturally make in the first year of life. Rocking, rolling, kicking, head-lifting, crawling: these aren’t random. They are the mechanism by which the brain matures and reflexes integrate. Each movement pattern stimulates specific brain regions (the brainstem, cerebellum, and vestibular system), driving neural development from the bottom up (Blomberg, 2015; Blomberg & Dempsey, 2011; Goddard, 2005).
Anything that disrupts this natural movement sequence can leave reflexes active. The most commonly identified disruption factors include:
A difficult or traumatic birth: cesarean delivery, vacuum extraction, cord complications, prolonged labor, all of which can stress the brainstem during the most vulnerable window.
Limited floor time in infancy and too much time in “containers” (car seats, bouncers, walkers, and swings) that restrict the whole-body movement the brain needs.
Illness or hospitalization in the early months.
Skipped crawling -the child who goes straight from sitting to walking, bypassing a critical stage of cross-body coordination.
Chronic stress in the home environment, because when the nervous system is in survival mode, development takes second priority.
Prenatal stress or maternal illness.
And various environmental factors (toxin exposure, food sensitivities, and nutritional deficits) that can interfere with neural maturation at the cellular level
(Goddard, 2005; Blomberg, 2015; Chandradasa & Rathnayake, 2020).
A note of importance here: this is not a blame list. Many of these factors are unavoidable, and many interventions that contribute to reflex retention (cesarean birth, neonatal hospitalization, the use of car seats) were done with the best intentions or were medically necessary. The point is not what went wrong. The point is that something can be done about it now, at any age, because the brain retains the capacity for reflex integration throughout the lifespan. And it’s worth noting that reflexes can also reactivate in older children and adults after trauma, injury, chronic illness, or sustained stress (Blomberg, 2015; Goddard, 2023).
The Developmental Hierarchy: A Map of the Brain
To understand why primitive reflexes matter so much, you need to understand how the brain develops. It builds from the bottom up. The deepest, most ancient structures mature first; the higher, more sophisticated structures develop later, on top of what’s already been built. Primitive reflexes correspond to specific levels of this architecture, and their integration — or retention — tells you something about how far the building process got before it stalled (Goddard, 2005; Blomberg, 2015).
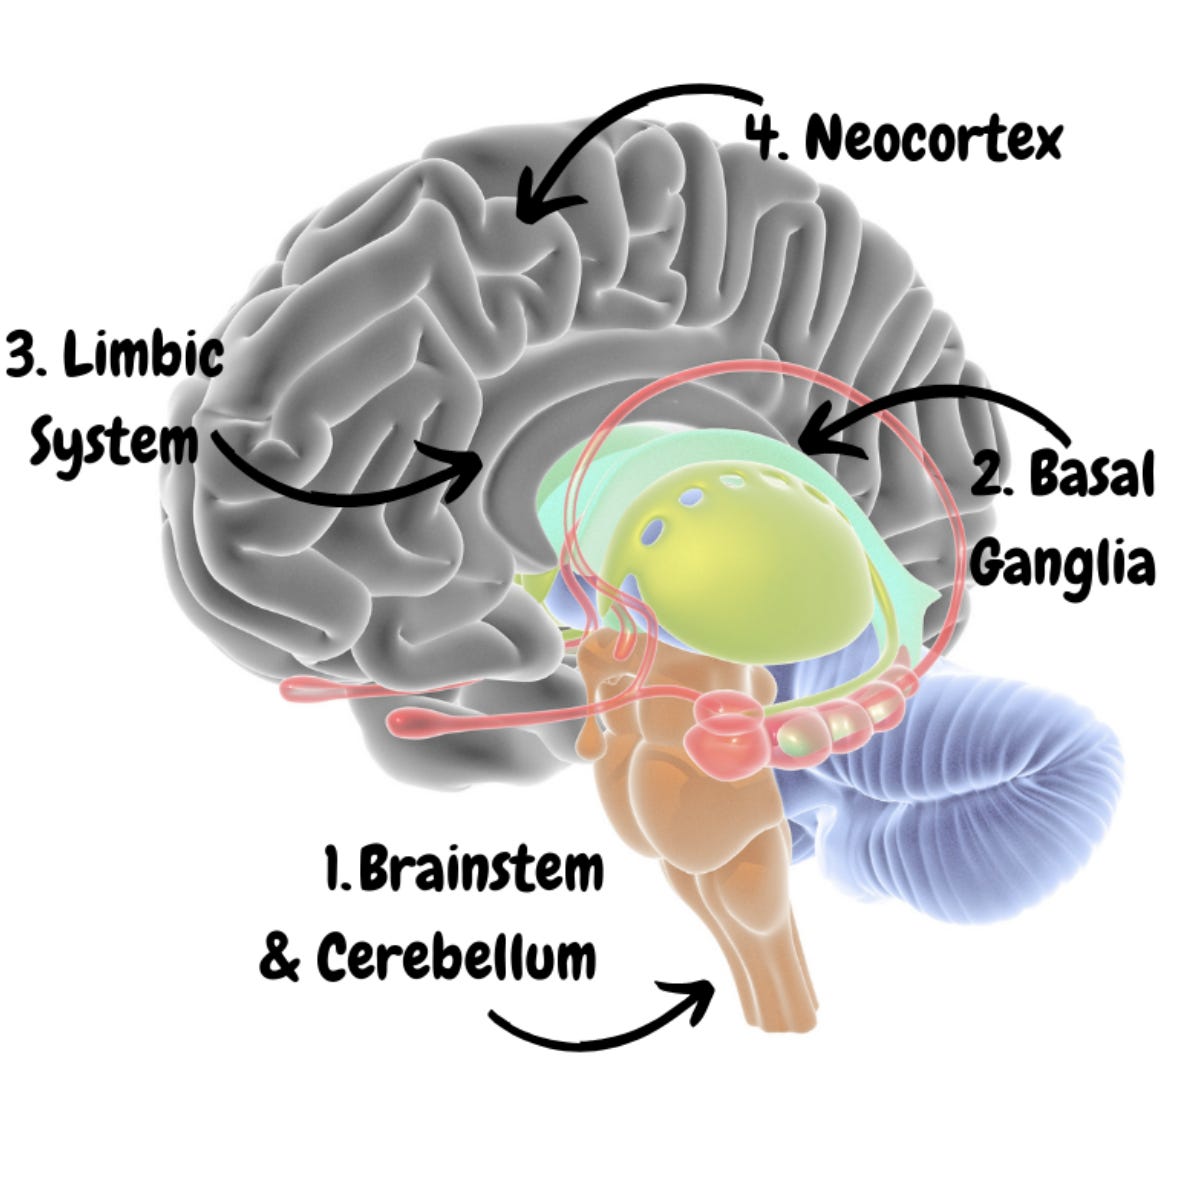
The Brainstem: The Survival Brain
The brainstem is the first structure to develop and the most primitive. It controls vital functions like breathing, heart rate, muscle tone, arousal, sleep-wake cycles; and it is where the earliest reflexes live. The Tonic Labyrinthine Reflex (TLR), the Spinal Galant, the Landau, the Babinski, the Symmetric Tonic Neck Reflex (STNR), and the Amphibian reflex are all brainstem-level patterns. When these remain active, you see issues with posture, muscle tone, balance, basic coordination, and the kind of foundational physical stability that everything else depends on (Blomberg, 2015; Goddard, 2005; Pecuch et al., 2021).
You can’t build a house on a shaky foundation ~ and you can’t build higher brain functions on an unfinished brainstem.
The Cerebellum and Basal Ganglia: The Coordination Center
Closely linked to the brainstem, the cerebellum and basal ganglia govern rhythm, timing, motor sequencing, and procedural learning. This is the kind of learning that allows a skill to become automatic. These structures are the reason Blomberg Rhythmic Movement Training uses rhythmic movement specifically: the rhythm stimulates these areas directly. When they are underdeveloped, you see clumsiness, poor timing, and a persistent inability to automate skills: reading stays effortful, handwriting never becomes fluent, tying shoes remains a conscious process years after peers have stopped thinking about it (Blomberg, 2015; Gieysztor et al., 2018).
The Limbic System: The Emotional Brain
The limbic system governs emotions, memory, social bonding, and stress regulation. It connects downward to the brainstem and upward to the prefrontal cortex; it is the bridge between the body’s survival machinery and the mind’s capacity for reflection and choice. The reflexes that most directly affect this level are the Fear Paralysis Reflex, the Moro reflex, and the Tendon Guard reflex, a.k.a. the “stress reflexes” that govern the freeze, fight-or-flight, and brace responses. When these remain active, we see anxiety, emotional reactivity, sensory overwhelm, difficulty with self-regulation, and the chronic autonomic dysregulation that we explored in our earlier posts on the FPR and Moro (Goddard, 2005; Blomberg, 2015; Porges, 2011).
The Neocortex: The Thinking Brain
The neocortex handles higher cognition: language, reading, writing, reasoning, visual processing. The reflexes that affect this level include the Asymmetric Tonic Neck Reflex (ATNR) and visual and articulatory reflexes. When these remain active, you see dyslexia-like symptoms, handwriting difficulties, letter reversals, visual tracking problems, and difficulty crossing the midline. But here is the crucial point: this level can only work well when the levels below it are stable. A child struggling with reading may have a neocortical reflex that needs attention, but if the brainstem and limbic foundations beneath it are still shaky, starting at the top is building on sand (Goddard, 2005; Blomberg, 2015; Chinello et al., 2018).
This hierarchy is why Harald Blomberg structured his training programs the way he did. BRMT Level 1 builds the brainstem and cerebellar foundation. Level 2 addresses the limbic and emotional layer. Level 3 tackles the neocortical and cognitive layer. You can’t skip levels. This mirrors how the brain itself develops and it means that the most effective approach begins at the bottom, even when the presenting problem appears to be at the top.

What Does a Retained Reflex Actually Look Like?
The clinical descriptions above are accurate, but they can be abstract. Here is what retained reflexes actually look like in real life, the moments when a parent, a teacher, a therapist, or an adult recognizing their own experience might think “wait, that’s exactly what I see”:
The child who W-sits and can’t keep their feet flat on the floor, whose core seems to have no power despite appearing physically healthy. This is often related to the Tonic Labyrinthine Reflex or Landau reflex, both of which affect muscle tone and postural stability (Goddard, 2005).
The child who cannot stop squirming, who hates tight waistbands, who wriggles out of every seat and cannot bear being lightly touched on the back. This constellation points to the Spinal Galant reflex, which is triggered by touch along the spine (Blomberg, 2015; Goddard, 2005).
The adult whose neck and shoulders are always tense, no matter how much stretching or massage they get. The tension returns within hours. This may be the Tendon Guard or TLR holding the upper body in a protective brace pattern that no amount of soft-tissue work will resolve because the instruction is coming from the brainstem, not the muscles (Blomberg, 2015).
The student who’s brilliant in conversation but falls apart on written tests. Verbally, she’s sharp. On paper, her letters reverse, her hand cramps, she loses her place. This gap between oral and written ability is a hallmark of a retained ATNR, which links head rotation to arm extension and interferes with the ability to look at a board and then write without involuntary movement disrupting the process (Goddard, 2005; Chinello et al., 2018).
The baby who startles at every sound and cannot settle. This is the Moro reflex, keeping the alarm system on full blast.
The child who freezes in new social situations or shuts down under pressure, a classic example of the Fear Paralysis Reflex, pulling the nervous system into withdrawal before conscious thought has any chance to intervene.
The person who gets carsick, hates elevators, or has poor spatial awareness: the TLR, disrupting the vestibular system’s relationship with gravity.
The kid who went straight from scooting to walking and now struggles with reading. The crawling stage that was skipped was the integration window for the STNR, a reflex intimately connected to eye tracking and upper-lower body coordination.
The toe-walker whose Babinski reflex may be keeping the feet in an extension pattern that was supposed to integrate in the first year of life (Goddard, 2005; Blomberg, 2015; Pecuch et al., 2021).
Each of these reflexes will get its own deep-dive post in this series. For now, the point is this: these aren’t character flaws, laziness, or “just anxiety.” They’re neurological patterns with names, explanations, and, most importantly, SOLUTIONS.
How Primitive Reflexes Integrate and How BRMT Helps
The Natural Process
In typical development, babies integrate their own reflexes through spontaneous rhythmic movement. The rocking, rolling, kicking, and head-lifting that infants do in their first months are not random, they are the brain’s self-building program. An estimated one million new neural connections form per second in the first three years of life, and the repetitive, rhythmic quality of infant movement is what drives this process, stimulating the brainstem, cerebellum, and vestibular system and pushing maturation upward through the hierarchy (Blomberg, 2015; Blomberg & Dempsey, 2011).
When the Process Was Incomplete, It Can Be Revisited
This is the foundational insight of Blomberg Rhythmic Movement Training (BRMT): the brain retains the capacity to integrate reflexes at any age. Neuroplasticity makes this possible. The same rhythmic movement patterns that drive reflex integration in infancy can be used with children, adolescents, adults, and the elderly to give the nervous system a second chance at completing the developmental sequence it missed the first time around (Blomberg, 2015).
Research supports this principle. Grigg and colleagues (2018) found that parents who used rhythmic movement training with their children reported it as easy to implement, cost-effective, and associated it with developmental and behavioral benefits. A follow-up quantitative study (Grigg et al., 2023) documented reduced reflex retention and improved reading scores in children who did just five minutes of rhythmic movement four times a week. Mohamed and colleagues (2023) found that reflex-integration approaches improved primitive reflex control and gross motor abilities in children with cerebral palsy. Melillo and colleagues (2022) documented the relationship between retained reflexes and functional brain disconnection in autism spectrum disorders, and proposed that targeted intervention could influence neural maturation, a finding supported by their subsequent work on hemispheric connectivity (Melillo et al., 2023; Leisman et al., 2023).
What BRMT Actually Looks Like
Because people often imagine something complicated or strenuous, it’s worth demystifying what BRMT actually involves. The movements are gentle, whole-body, and rhythmic — rocking, sliding, and rolling patterns done on the floor. They can be passive (someone else moves you) or active (you move yourself). In addition to the rhythmic movements, BRMT includes isometric pressure techniques specific to each reflex, which support the brainstem in releasing the reflex pattern.
Sessions typically begin at one to two minutes per day. The principle is “less is more” — the nervous system needs time to process the input, and doing too much too fast can overwhelm the system rather than support it. Because the movements are based on innate developmental patterns, the central nervous system recognizes them, and change can sometimes be observed remarkably quickly (Blomberg, 2015).
BRMT is not forceful or painful. It is not exercise in the fitness sense. It is not something you need to do for hours. It’s not a “3 sets of 10 reps each” kind of thing. And it is not a replacement for medical care. However, it addresses root causes that other approaches often miss, because most interventions target the symptoms of retained reflexes without anyone identifying the reflex itself.
The approach was developed by Dr. Harald Blomberg, a Swedish psychiatrist, based on decades of clinical observation and the foundational work of Kerstin Linde. It is now practiced worldwide by therapists, educators, and parents, and it remains the only reflex integration program that spans the full lifespan — from premature infants to the elderly (Blomberg, 2015; Blomberg & Dempsey, 2011).
The Deeper Story: Why Reflexes May Matter More Than We Thought
If you’ve been following this series, you’ve already encountered the idea that primitive reflexes don’t just affect movement and behavior, they may interface with the body’s deepest stress-response architecture, all the way down to the cellular and subcellular level.
In our posts on the Fear Paralysis Reflex and the Moro reflex, we explored the connections between retained reflexes, autonomic nervous system regulation, and Robert Naviaux’s Cell Danger Response (CDR), the universal metabolic reaction by which cells shift into a defensive configuration when mitochondria detect threat (Naviaux, 2014; Naviaux, 2023). The FPR’s whole-body freeze parallels the CDR’s whole-cell freeze. The Moro’s chronic sympathetic activation drives the kind of cortisol cycling that damages mitochondria and triggers the CDR. Naviaux’s 2023 work formally integrated the CDR framework with Polyvagal Theory, placing mitochondrial danger signaling under brainstem control, the same brainstem that governs primitive reflexes (Naviaux, 2023; Porges, 2011).
This convergence is still emerging and has not been directly tested, but the physiological logic is coherent: if the brainstem is the master switch governing both reflex state and cellular threat response, then approaches that address brainstem regulation, like rhythmic movement training, may influence not only reflexes and behavior but the metabolic environment of the body’s cells. That possibility reframes reflex integration from a niche developmental therapy into something potentially relevant for anyone dealing with chronic stress, fatigue, immune dysfunction, or the constellation of symptoms that accompany a body stuck in defense mode.
We’ll continue exploring these connections throughout this series, including a dedicated post proposing a possible mechanism of action for how rhythmic movement works at the cellular level.
How to Use This Series
This post is your reference point — the one you can come back to whenever you want to remember what a particular reflex does or where it sits in the developmental hierarchy. The rest of the series will give each major reflex its own deep-dive post, following the brain’s own developmental sequence: foundation reflexes first (posture, tone, coordination), then the emotional reflexes (stress, fear, regulation), then the cognitive reflexes (vision, reading, writing).
Along the way, we’ll explore specialized topics: the role of diet and inflammation, the unique considerations for babies, the experience of adults encountering reflex integration for the first time, and the surprising emotional dimensions that integration work can stir up.
For now, I’d invite you to do something simple: start noticing. Which descriptions in this post resonated? Which patterns do you recognize in yourself, your child, your students, or your clients? You don’t need to diagnose anything. Just notice. That’s your starting point.
A Different Question
Let’s return to where we began.
The fidgeting child. The tense adult. The struggling writer. The joint replacement. The overwhelmed toddler.
They don’t need to be “fixed.” Their nervous systems are doing exactly what retained reflexes tell them to do. The child isn’t choosing to squirm. The adult isn’t choosing tension. The teenager isn’t choosing to fail the exam. The knee joint isn’t choosing to degenerate. And the toddler isn’t choosing to be terrified of the blender. These are brainstem-level patterns operating below conscious control, and they have been operating since before any of these individuals had words to describe what was happening to them.
The question isn’t “what’s wrong with them?” It’s “what reflex pattern is still running, and how do we help it complete its job?”
Because we’re looking at a brainstem-level presentation, you can’t “mindset” your way out of a retained reflex.
I’d like to propose a reframe: from brokenness to incompleteness, from pathology to interrupted development. This is what this entire series is about. Because when a primitive reflex integrates, it doesn’t just resolve one symptom. It changes the foundation. And when the foundation changes, everything built on top of it gets a chance to reorganize.
If you recognized someone you love in these descriptions — or yourself — I’d welcome a conversation. Primitive reflex assessment is straightforward, and Blomberg Rhythmic Movement Training provides a gentle, evidence-informed path toward completing what the nervous system started. You are welcome to schedule a consultation to explore whether retained reflexes may be part of the picture, and what integration might look like for you or your child.
Learn This Work From the Inside Out

If this knowledge has you wanting to move beyond reading and into practice, I’m teaching BRMT Level 1 this summer. Online (via Zoom), over eight Monday evenings (June–July, 6:30–8:30 PM ET), you’ll learn the foundational reflexes, how to test for them, and the specific rhythmic movements and isometric techniques used to integrate them. Whether you’re a parent, therapist, educator, or someone who simply recognizes these patterns in your own body, this course gives you the tools to work with them directly. No prerequisites. Just curiosity and a willingness to get on the floor.
Ready to join? Register via the link below. A $100 non-refundable deposit secures your spot, and the remaining $295 will be billed after sign-up. The full course cost of $395 includes your printed manual, which will be mailed to you upon registration.
Once you click the link below, from the dropdown menus, select:
Payment: non-refundable deposit
Taught By: Dr. Amanda Conta Steencken
Date & Location: Weekly online sessions from June 1 - July 20th, 6:30-8:30pm ET
Thanks so much for being here!
much love,
Amanda
PS: If this shifted something for you, the paid tier is where we go deeper. Each month, paid subscribers get the practices, the movement demonstrations, and the detailed protocols that turn these ideas into felt change in your body. It’s $20/month or $200/year - less than a single copay.
References
Arcilla, C.K. & Vilella, R.C. (2025). Tonic Neck Reflex. In StatPearls. StatPearls Publishing. http://www.ncbi.nlm.nih.gov/books/NBK559210/
Blomberg, H. (2015). The Rhythmic Movement Method: A Revolutionary Approach to Improved Health and Well-Being. CreateSpace Independent Publishing Platform.
Blomberg, H. & Dempsey, M. (2011). Movements that Heal: Rhythmic Movement Training and Primitive Reflex Integration. Beyond the Sea Squirt.
Capute, A.J., Accardo, P.J., Vining, E.P.G., Rubenstein, J.E., & Harryman, S. (1978). Primitive reflex profile. Physical Therapy, 58(9), 1061–1065. doi: 10.1093/ptj/58.9.1061
Chandradasa, M. & Rathnayake, L. (2020). Retained primitive reflexes in children: clinical implications and targeted home-based interventions. Nursing Children and Young People, 32(1), 37–42. doi: 10.7748/ncyp.2019.e1132
Chinello, A., Di Gangi, V., & Valenza, E. (2018). Persistent primary reflexes affect motor acts: potential implications for autism spectrum disorder. Research in Developmental Disabilities, 83, 287–295. doi: 10.1016/j.ridd.2016.07.010
Gieysztor, E.Z., Choinska, A.M., & Paprocka-Borowicz, M. (2018). Trunk rotation due to persistence of primitive reflexes in early school-age children. Advances in Clinical and Experimental Medicine, 27(3), 363–366. doi: 10.17219/acem/67458
Goddard, S. (2005). Reflexes, Learning and Behavior: A Window into the Child’s Mind (2nd ed.). Fern Ridge Press.
Goddard Blythe, S. (2023). Reflexes, Movement, Learning & Behaviour: Analysing & Unblocking Neuro-Motor Immaturity. Hawthorn Press.
Grigg, T.M., Fox-Turnbull, W., & Culpan, I. (2018). Retained primitive reflexes: perceptions of parents who have used rhythmic movement training with their children. Journal of Child Health Care, 22(3), 406–418. doi: 10.1177/1367493518760736
Grigg, T.M., Culpan, I., & Fox-Turnbull, W. (2023). Primitive reflex integration and reading achievement in the classroom. Journal of Neurology and Experimental Neuroscience, 9(1). doi: 10.17756/jnen.2023-103
Leisman, G., Machado, C., Melillo, R., & Mualem, R. (2023). Prefrontal functional connectivities in autism spectrum disorders: a connectopathic disorder affecting movement, interoception, and cognition. Brain Research Bulletin, 198, 65–76. doi: 10.1016/j.brainresbull.2023.04.004
Melillo, R., Leisman, G., Machado, C., et al. (2022). Retained primitive reflexes and potential for intervention in autistic spectrum disorders. Frontiers in Neurology, 13, 922322. doi: 10.3389/fneur.2022.922322
Melillo, R., Leisman, G., Machado, C., et al. (2023). The relationship between retained primitive reflexes and hemispheric connectivity in autism spectrum disorders. Brain Sciences, 13(8), 1147. doi: 10.3390/brainsci13081147
Mohamed, M.A., et al. (2023). Sensory integration versus Masgutova Neuro-Sensorimotor Reflex Integration program on controlling primitive reflexes and gross motor abilities in children with diplegic cerebral palsy. Physiotherapy Research International, 28(4), e2030. doi: 10.1002/pri.2030
Naviaux, R.K. (2014). Metabolic features of the cell danger response. Mitochondrion, 16, 7–17. doi: 10.1016/j.mito.2013.08.006
Naviaux, R.K. (2023). Mitochondrial and metabolic features of salugenesis and the healing cycle. Mitochondrion, 70, 131–163. doi: 10.1016/j.mito.2023.04.003
Pecuch, A., Gieysztor, E., Telenga, M., Wolanski, P., & Paprocka-Borowicz, M. (2021). Primitive reflex activity in relation to motor skills in healthy preschool children. Brain Sciences, 11(8), 967. doi: 10.3390/brainsci11080967
Porges, S.W. (2011). The Polyvagal Theory: Neurophysiological Foundations of Emotions, Attachment, Communication, and Self-Regulation. W.W. Norton & Company.
Zafeiriou, D.I. (2004). Primitive reflexes and postural reactions in the neurodevelopmental examination. Pediatric Neurology, 31(1), 1–8. doi: 10.1016/j.pediatrneurol.2004.01.012